Hidden Immune Cells Offer New Hope Against the Deadliest Lung Cancer
WEHI researchers have discovered that gamma delta T cells can recognise and kill small cell lung cancer, and that two existing drugs can boost this immune attack, opening a promising new treatment avenue for the deadliest form of lung cancer.
Small cell lung cancer has long been one of the most formidable opponents in oncology, a disease that accounts for roughly fifteen percent of lung cancer cases yet claims a disproportionate share of lives. With a five-year survival rate of less than seven percent, it stands as the most aggressive and least treatable form of lung cancer worldwide.
Now, researchers at the Walter and Eliza Hall Institute (WEHI) in Australia have identified a previously overlooked ally in the fight against this disease: a specialised population of immune cells known as gamma delta T cells. Published in the journal Cancer Cell, the study provides the strongest evidence to date that these cells are present in small cell lung tumours and appear capable of recognising and destroying cancer cells that have otherwise mastered the art of immune evasion.
The central problem that has stymied treatment efforts for decades is invisibility. Immunotherapy, which has revolutionised outcomes in melanoma and other cancers, works primarily by unleashing conventional immune cells, most notably alpha beta T cells, to attack tumours. But small cell lung cancer is exceptionally adept at hiding from these standard immune defenders.
The tumours present few of the molecular flags that conventional T cells need to identify a target, and only a rare subset of patients derives long-term benefit from checkpoint inhibitor drugs. This immune invisibility is a major reason why advances in small cell lung cancer treatment have been so scarce, and why the disease has seen few meaningful therapeutic improvements over the past several decades.
Gamma delta T cells offer a fundamentally different route of attack. Unlike their alpha beta counterparts, these cells recognise targets through distinct sensing mechanisms that do not depend on the usual antigen-presenting machinery, allowing them to detect stressed or transformed cells through patterns that tumours find harder to conceal.
The WEHI team, led by senior author Professor Kate Sutherland, found that patients whose tumours contained higher levels of gamma delta T cells tended to live longer, a correlation that suggests these cells constitute a genuine, functional line of anti-cancer defence rather than a passive presence.
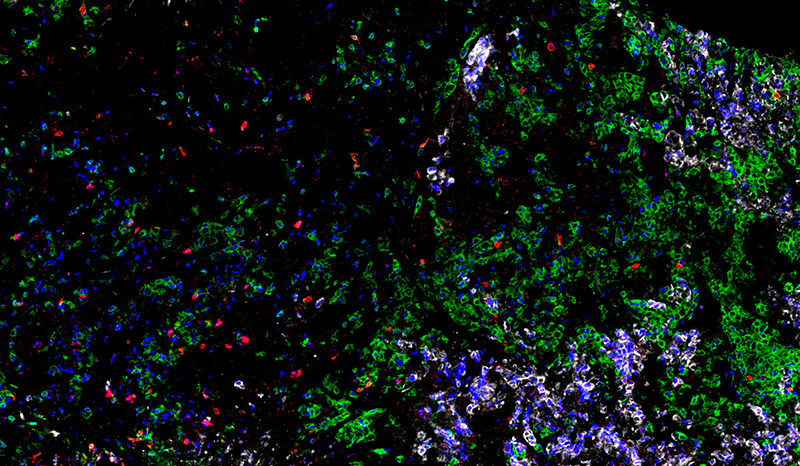
In tissue samples taken from long-term survivors, the researchers could see gamma delta T cells infiltrating the tumour, in direct contact with the cancer cells they appeared to be attacking. To test this potential rigorously, the team turned to an innovative laboratory platform: miniature tumours, or organoids, grown from patient-donated samples.
These samples were provided through the Victorian Cancer Biobank in collaboration with the Royal Melbourne Hospital, and the resulting mini tumours represent one of the most realistic laboratory models of small cell lung cancer developed to date. Because they preserve the cellular and molecular complexity of the original patient tumours, they offer a far more faithful testing ground than traditional two-dimensional cell cultures.
When the researchers combined these mini tumours with gamma delta T cells harvested from the same patients’ blood, the immune cells proved highly effective at recognising and killing the SCLC cells, even when the disease had adopted its usual camouflage. Perhaps the most clinically exciting discovery is that the cancer-killing activity of these cells can be amplified using drugs that already exist.
The team identified two approved therapies that, in combination, dramatically strengthened the gamma delta T cell response. The first, zoledronate, is a bisphosphonate already approved for osteoporosis and cancer-related bone disease. In the study, zoledronate increased the number of gamma delta T cells available and enhanced their ability to recognise the tumours.
The second, tarlatamab, is a bispecific antibody recently approved as a cancer treatment for small cell lung cancer itself. Tarlatamab acted, in the researchers’ description, like a magnetic force, physically drawing the immune cells into closer contact with the cancer cells so that the killing could proceed efficiently.
The synergy between these two agents points toward a rational combination strategy. Zoledronate effectively primes and expands the gamma delta T cell population, while tarlatamab bridges the gap between immune cell and tumour, ensuring that the activated killers reach their targets.
Together, the drugs significantly enhanced the ability of gamma delta T cells to attack cancer cells in the laboratory models. Because both drugs are already approved for human use, albeit for different indications, the path from laboratory finding to clinical testing could be considerably shorter than for an entirely novel therapy.
This repurposing opportunity is what gives the discovery its immediate translational appeal. Dr Jin Ng, first author on the paper, highlighted another promising dimension: adoptive cell transfer. This approach, already proven with CAR-T therapies in blood cancers, involves collecting a patient’s immune cells, growing them to large numbers outside the body, and infusing them back into the patient.
As Ng noted, therapies that expand and reinfuse gamma delta T cells already exist, raising the possibility of rapidly translating the current findings into new treatment strategies. For patients whose tumours contain low levels of gamma delta T cells, drugs such as zoledronate might first boost their native population of cancer-fighting cells, improving their responsiveness to existing treatments.
The researchers suggest this could open an entirely new avenue for personalised treatment approaches, not only in small cell lung cancer but potentially in other solid cancers that evade conventional immune surveillance. A crucial part of the evidence base came from an unexpected source: landmark clinical trials.
Rather than starting from scratch, the team analysed data from IMpower133 and CASPIAN, the two practice-changing trials that established immunotherapy as a standard of care for small cell lung cancer. Using advanced genomic and computational analyses conducted by WEHI’s genomics and bioinformatics teams, the researchers searched for immune signatures associated with exceptional treatment responses.
What emerged was a clear pattern: patients who experienced the greatest benefit from immunotherapy carried a strong gamma delta T cell signature in their tumours. This retrospective human evidence, combined with the functional organoid experiments, forms a compelling two-pronged case that these cells matter clinically, not merely in theory.
The implications extend beyond a single cancer type. Small cell lung cancer is a neuroendocrine malignancy characterised by rapid growth, early metastasis, and a tumour microenvironment that suppresses conventional immunity. If gamma delta T cells can see through that suppression, the same logic may apply to other tumours that are similarly invisible to standard immunotherapy, a category that includes many of the hardest-to-treat solid cancers.
The WEHI team, working in an ongoing collaboration with researchers at the Doherty Institute, now hopes to translate the findings into a new class of immunotherapy drugs for small cell lung cancer. The research was supported by Cancer Council Victoria, the National Health and Medical Research Council, The CASS Foundation, and the International Association for the Study of Lung Cancer.
For a disease that has remained stubbornly resistant to progress, the study offers something rare: a concrete, testable mechanism that connects immune biology to patient survival and points to drugs that are already on pharmacy shelves. Much work remains before gamma delta T cell-based strategies reach the clinic, including formal clinical trials to establish safety and efficacy in small cell lung cancer patients.
But the convergence of patient-derived organoid data, clinical trial evidence, and repurposable approved drugs gives this discovery a momentum that few laboratory findings achieve. After decades in which small cell lung cancer successfully hid from the immune system and from therapeutic innovation alike, one of its most effective disguises may finally have been seen through.
Subject of Research: Gamma delta T cell immunity and drug-enhanced immunotherapy for small cell lung cancer Article Title: Invisible no more: New treatment avenue unlocked for deadliest lung cancer Article References: Invisible no more: New treatment avenue unlocked for deadliest lung cancer. (n.d.).
Original publication Image Credits: AI Generated DOI: Not provided Keywords: small cell lung cancer, gamma delta T cells, immunotherapy, organoids, zoledronate, tarlatamab, cancer immunology, WEHI, Cancer Cell, adoptive cell therapy, tumour immune evasion, drug repurposing
Article text via FreeNewsAPI. Rights remain with Bioengineer.org.
Read on publisher site → Opens Bioengineer.org in a new tab